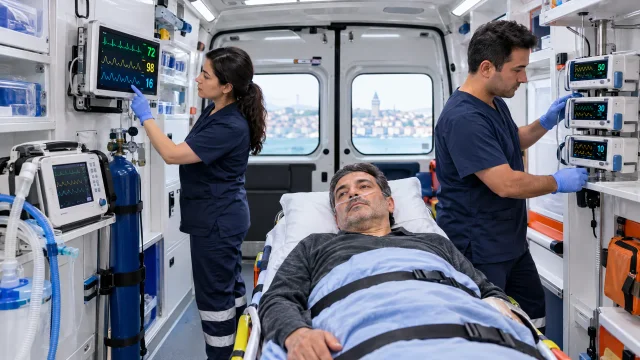
When Is a Doctor-Led Ambulance Needed?
When is a doctor-led ambulance needed? Criteria for high-risk transfers and events, and how to request a physician for your transfer, 24/7.
- Medical review
- Nova Ambulans Sağlık Kurulu (Medical Board)Prepared with input from the Medical Board. AI-assisted draft.
- Published
- Last reviewed
- Reading time
- 8 min
Key takeaways
- Physician accompaniment is considered for clinically unstable or high-risk patients.
- Complex transfers may require expanded intervention capability during transit.
- Early clinical briefing helps select the correct team model.
In this article (10 sections)
- How Is the Physician Accompaniment Decision Made?
- Physician Accompaniment Across 7 Patient Categories
- Doctor vs. Paramedic Comparison
- SpO2 Thresholds and Crew Decision
- Physician Accompaniment Decision Summary
- Field Scenarios — When Physician Accompaniment Is Needed
- Why Clinical Triage Before Transport Is Essential
- Physician Accompaniment at Events
- Frequently Asked Questions
- Sources
Physician accompaniment is not required for every patient transfer. For stable, planned transports, a team of a paramedic and driver may be sufficient. However, for patients at risk of clinical deterioration during transit, physician accompaniment makes a decisive difference. In what is often called a "doctor-led ambulance", the vehicle stays the same: all Nova Ambulans vehicles are ICU-equipped Emergency Ambulances (Acil Yardım Ambulansı) 7; a physician is added on request. This guide reviews when physician accompaniment is needed, together with the clinical warning signs the physician weighs.
How Is the Physician Accompaniment Decision Made?
The decision is based less on the diagnosis and more on the level of clinical risk during transit. The key question is: "Is there a risk of clinical deterioration during transport, and would physician intervention be required if it occurs?"
Clinical Decision Parameters
The following are general warning signs. If one or more is present, physician accompaniment is usually recommended:
- GCS (Glasgow Coma Scale): below 13 or fluctuating
- SpO2: below 92% or requiring support
- Systolic blood pressure: below 90 mmHg or unstable
- Heart rate: below 40 or above 130
- Respiratory rate: below 10 or above 30
- Active IV drug infusion in progress
These values are general guidance, not fixed cut-offs; the final decision on the transfer team is made by the physician assessing the patient.
Physician Accompaniment Across 7 Patient Categories
1. Patients Requiring Respiratory Support
The need for respiratory support is one of the strongest indications for physician accompaniment. 7
- Mechanically ventilated patients: Ventilator settings may need to be changed during transit. This authority belongs to a physician only.
- Advanced oxygen needs: Patients on high-flow nasal cannula (HFNC), CPAP, or BiPAP.
- SpO2 instability: Patients trending toward oxygen saturation below 92%.
- Tracheostomy patients: Cannula change or suctioning may be required.
2. Patients with Variable Level of Consciousness (GCS)
The GCS score is a critical indicator for assessing the risk level during transit. The table below is general guidance; the treating physician decides for each patient.
| GCS Range | Risk Level | Crew Recommendation |
|---|---|---|
| 15 (full consciousness) | Low | Paramedic sufficient |
| 13-14 (mild impairment) | Moderate | Decide per clinical assessment |
| 9-12 (moderate impairment) | High | Physician accompaniment recommended |
| 3-8 (severe impairment) | Critical | Physician accompaniment strongly recommended |
- Sedated patients: Monitoring sedation depth and intervening when needed requires a physician.
- Confusion or agitation: Risk of self-harm or harm to the crew may require physician assessment.
- Risk of neurological deterioration: In post-stroke, post-neurosurgery, or epilepsy patients.
3. High-Risk Post-Operative Patients
Transfers in the early period after major surgery carry a risk of complications. 7
- Major surgery: After open-heart, brain, thoracic, or abdominal surgery.
- Anesthesia effect: Patients not fully recovered from general anesthesia; risks of respiratory depression, nausea-vomiting, and altered consciousness.
- Active pain management: Patients on ongoing IV analgesic infusion with uncontrolled pain.
- Surgical complication risk: Possibility of early complications such as bleeding, wound dehiscence, or pneumothorax.
4. Elderly Patients with Multiple Comorbidities
The geriatric population is the most fragile group at risk of decompensation during transit.
- Multiple chronic conditions: Combinations such as diabetes + hypertension + heart failure + COPD.
- Polypharmacy: Patients on 5 or more medications; risk of drug interactions and side effects.
- Frailty: Poor general condition, high risk of falls and decompensation.
- Cognitive impairment: Patients with dementia or Alzheimer's; transit stress can trigger agitation.
5. Patients Requiring Cardiac Monitoring
Cardiac monitoring requires a physician's ECG interpretation and intervention competence.
- Cardiac rhythm disturbance: Arrhythmias such as atrial fibrillation or ventricular tachycardia.
- Blood pressure instability: Hypertensive crisis or hypotension tendency.
- Recent cardiac event: After myocardial infarction, angioplasty, or stenting.
- Heart failure: Decompensated heart failure with respiratory distress and edema.
6. Post-Anesthesia Transport
The recovery process from anesthesia carries respiratory and hemodynamic risks.
- Respiratory depression: Residual effect of anesthetic agents.
- Nausea-vomiting: Risk of aspiration.
- Hypotension: Post-anesthesia vasodilation.
- Thermoregulation disturbance: Risk of hypothermia.
7. Patients Dependent on Drains, Catheters, or Infusions
Patients dependent on medical devices carry a risk of technical complications during transit.
- Chest drain (thoracic tube): Safe management of the drainage system during transit.
- Urinary catheter: Risk of infection and mechanical complications.
- Nasogastric tube: Aspiration risk and feeding-pump management.
- Continuous IV drug infusion: A paramedic may run an infusion at the doses and indications in approved protocol flowcharts; however, off-protocol dose titration (e.g. adjusting a continuous vasopressor/sedative infusion) requires a physician's order/authority. 7
- Epidural catheter: Pain management and neurological monitoring.
Doctor vs. Paramedic Comparison
| Authority/Capability | Paramedic (Ambulance and Emergency Care Technician, AABT) | Doctor |
|---|---|---|
| Basic Life Support | Yes | Yes |
| Advanced Life Support | Yes (within protocol) | Yes (full authority) |
| IV drug administration | Limited within protocol | Broad drug range |
| Clinical decision-making | Within protocol | Full authority |
| ECG interpretation | Basic rhythm recognition | Advanced ECG analysis |
| Sedation management | No | Yes |
| Changing ventilator settings | No | Yes |
| Changing the treatment plan | No | Yes |
| Intubation | Within protocol | Full authority |
| Drug dose change (off-protocol titration) | No | Yes |
| Surgical intervention (emergency) | No | Limited (e.g. cricothyrotomy) |
SpO2 Thresholds and Crew Decision
| SpO2 Value | Clinical Meaning | Crew Recommendation |
|---|---|---|
| 95-100% | Normal | Paramedic sufficient |
| 92-94% | Mild hypoxia | Decide per clinical assessment |
| 88-91% | Moderate hypoxia | Physician accompaniment recommended |
| <88% | Severe hypoxia | Physician accompaniment; consider ICU-level monitoring |
These ranges are general guidance. For patients with chronic lung disease such as COPD, the physician may set a different individual target, and the final crew decision rests with the physician assessing the patient.
Physician Accompaniment Decision Summary
The summary below is general guidance; the referring or treating physician makes the final decision.
| Patient Profile | Risk Level | Physician Accompaniment? |
|---|---|---|
| Stable, conscious, planned check-up | Low | Not required |
| Oxygen support, single IV drug | Moderate | Recommended |
| GCS <13, SpO2 <92% | High | Strong recommendation |
| Ventilator-dependent | Critical | Required (consider ICU-level monitoring) |
| Post-operative, anesthesia effect ongoing | High | Strong recommendation |
| Multiple comorbidity, polypharmacy | Moderate-High | Recommended |
| Cardiac arrhythmia, unstable blood pressure | High | Strong recommendation |
Field Scenarios — When Physician Accompaniment Is Needed
The European Society of Cardiology (ESC) and American Heart Association (AHA) pre-hospital care guidelines emphasize that advanced life support capability is delivered through team composition, not just vehicle class 16.
Scenario A — Sedated, Ventilated Patient on Inter-Hospital Transfer
A 71-year-old transferred from a private ICU on the European side to a higher-acuity center on the Anatolian side, on propofol infusion, FiO₂ 0.6, PEEP 8 cmH₂O. A paramedic-only crew is insufficient: in-transit sedation depth adjustment, ventilator parameter changes, and possible vasopressor titration require physician authority 17. Nova Ambulans dispatches a physician-accompanied crew with a transport ventilator and syringe pumps for this transfer.
Scenario B — Acute Coronary Syndrome with Cardiac Monitoring
A patient presenting to an outpatient clinic in Istanbul with dynamic ST changes on ECG is referred to a PCI-capable center. The American Heart Association (AHA) Mission: Lifeline program documents that pre-hospital 12-lead ECG and continuous rhythm monitoring shorten door-to-balloon time meaningfully 6. The Nova Ambulans physician-accompanied crew can administer IV nitrate, antiplatelets, and antiarrhythmics if needed.
Scenario C — Febrile Neutropenia After Chemotherapy
A chemotherapy patient discharged from an oncology center develops 38.5 °C fever, hypotension, and mucositis, requiring transport to a competent center rather than home. Sepsis risk and the need to start IV antibiotics justify physician-led transport 34. With a physician on board, fluid resuscitation, oxygen support, and early antibiotic therapy can be initiated.
Physician Accompaniment at Nova Ambulans
The Nova Ambulans operations center prepares physician-accompanied crews 24 hours ahead for planned transfers and quickly after clinical briefing for urgent referrals. Physician accompaniment can be requested across Istanbul, on long-distance intercity routes, and for inter-hospital transfers; the decision is finalized with the family alongside the referring physician's discharge summary.
Why Clinical Triage Before Transport Is Essential
A short triage briefing before dispatch helps determine:
- Team structure
- Device and medication readiness
- Monitoring level during transfer
- Handover protocol at destination
This reduces unexpected escalation during transit and supports continuity of care.
For ventilated, sedated, or cardiac-monitored transfers, share the discharge summary with the Nova Ambulans operations center; we will plan the physician-accompanied crew, transport ventilator, and infusion-pump configuration across Istanbul. Call us 24/7 at 0216 339 00 39 or message us on WhatsApp at 0549 461 34 00; share the patient's condition and we will plan the crew. A physician joins on request.
Physician Accompaniment at Events
At high-risk events (large concerts, sports organizations, festivals), adding a physician to the ambulance crew increases active medical intervention capacity. 7
Event Profiles Requiring Physician Accompaniment
- 5,000+ attendee large organizations
- High physical risk: extreme sports, water sports, motorsports
- Long-duration events: festivals lasting more than 8 hours
- High alcohol consumption: concerts, night events
- Special populations: elderly attendees or disabled-sports organizations
In environments requiring crowd management, trauma response, and rapid clinical decision-making, physician leadership is critical.
Frequently Asked Questions
Is physician accompaniment needed for every elderly patient?
No. For elderly patients who are stable, sufficiently mobile, and traveling to a planned check-up, a standard team may be sufficient. If there is multiple comorbidity, fall risk, or altered consciousness, physician accompaniment is recommended.
Does physician accompaniment make the transfer more expensive?
Yes, physician accompaniment adds cost. However, cost should be weighed against the patient's clinical need. Complications during an under-resourced transfer carry a far greater risk.
Who requests physician accompaniment?
Family members can request it directly. Ideally, however, the discharging or referring physician advises on the transfer team. The Nova Ambulans operations team recommends the appropriate crew based on the patient's information.
Is a paramedic crew insufficient?
Paramedics are health professionals competent in Advanced Life Support. For stable patients, planned transfers, and low-risk transports, a paramedic crew is entirely sufficient. Physician accompaniment is needed for cases with a high clinical risk level.
Does the discharging doctor advise on the transfer team?
Yes, the discharging physician can and should advise on the transfer team based on the patient's clinical condition. A note such as "transfer with physician accompaniment is recommended" frequently appears in the discharge summary.
Which drugs can be administered when a physician accompanies the transfer?
The physician can draw on a broad range of drugs based on clinical need: IV analgesics, antiemetics, antihypertensives, antiarrhythmics, sedatives, bronchodilators, and emergency cardiac drugs. 7
Is physician accompaniment always safer?
Not automatically. Safety depends on matching team capability to the patient's actual risk profile.
Can a physician be added to a transfer during planning?
Yes. If risk indicators are identified early, the crew configuration can be adjusted before dispatch.
Sources
Numbers in the text refer to the sources below.
- ESC Clinical Practice Guidelines (opens in a new tab)European Society of Cardiology (ESC)
- AAFP Clinical Recommendations for Acute and Chronic Conditions (opens in a new tab)American Academy of Family Physicians (AAFP)
- Emergency and Critical Care (opens in a new tab)World Health Organization (WHO)
- AHA — Mission: Lifeline (Pre-hospital Cardiac Care) (opens in a new tab)American Heart Association
Nova Ambulans Sağlık Kurulu (Medical Board)
Periodically reviewed by our editorial board of emergency physicians, paramedics and clinical coordinators.
This content is informational only and does not replace professional medical evaluation. In emergencies, call 112 or +90 216 339 00 39.